Positive Findings (Patient Has This)
| Finding | Increased Disease Probability (Positive Likelihood Ratio) |
|---|---|
| Chest radiography | |
| Kerley B lines | |
| Interstitial edema | |
| Cephalization | |
| Alveolar edema | |
| Lung ultrasonography | |
| Positive B-line scan | |
| Bedside echocardiography | |
| Restrictive mitral pattern | |
Negative Findings (Patient Doesn't Have This)
| Finding | Decreased Disease Probability (Negative Likelihood Ratio) |
|---|---|
| Chest radiography | |
| Kerley B lines | |
| Interstitial edema | |
| Cephalization | |
| Alveolar edema | |
| Lung ultrasonography | |
| Positive B-line scan | |
| Bedside echocardiography | |
| Restrictive mitral pattern | |
Narrative
This review included 57 mostly prospective or cross-sectional studies, 52 unique cohorts, and a total of 17,893 patients.2 There was no single historical variable, symptom, or physical examination finding that could significantly reduce the likelihood of AHFS. An S3 gallop marginally increased the likelihood of AHFS (positive likelihood ratio [LR+] = 4.0; 95% confidence interval [CI], 2.7 to 5.9) but was an insensitive finding. None of the abnormal ECG findings substantially increased or decreased the probability of AHFS. The presence of radiographic findings that represented edema moderately increased the likelihood of AHFS (LR+ = 4.8 to 6.5; Table 1), but a negative chest radiograph was unhelpful.
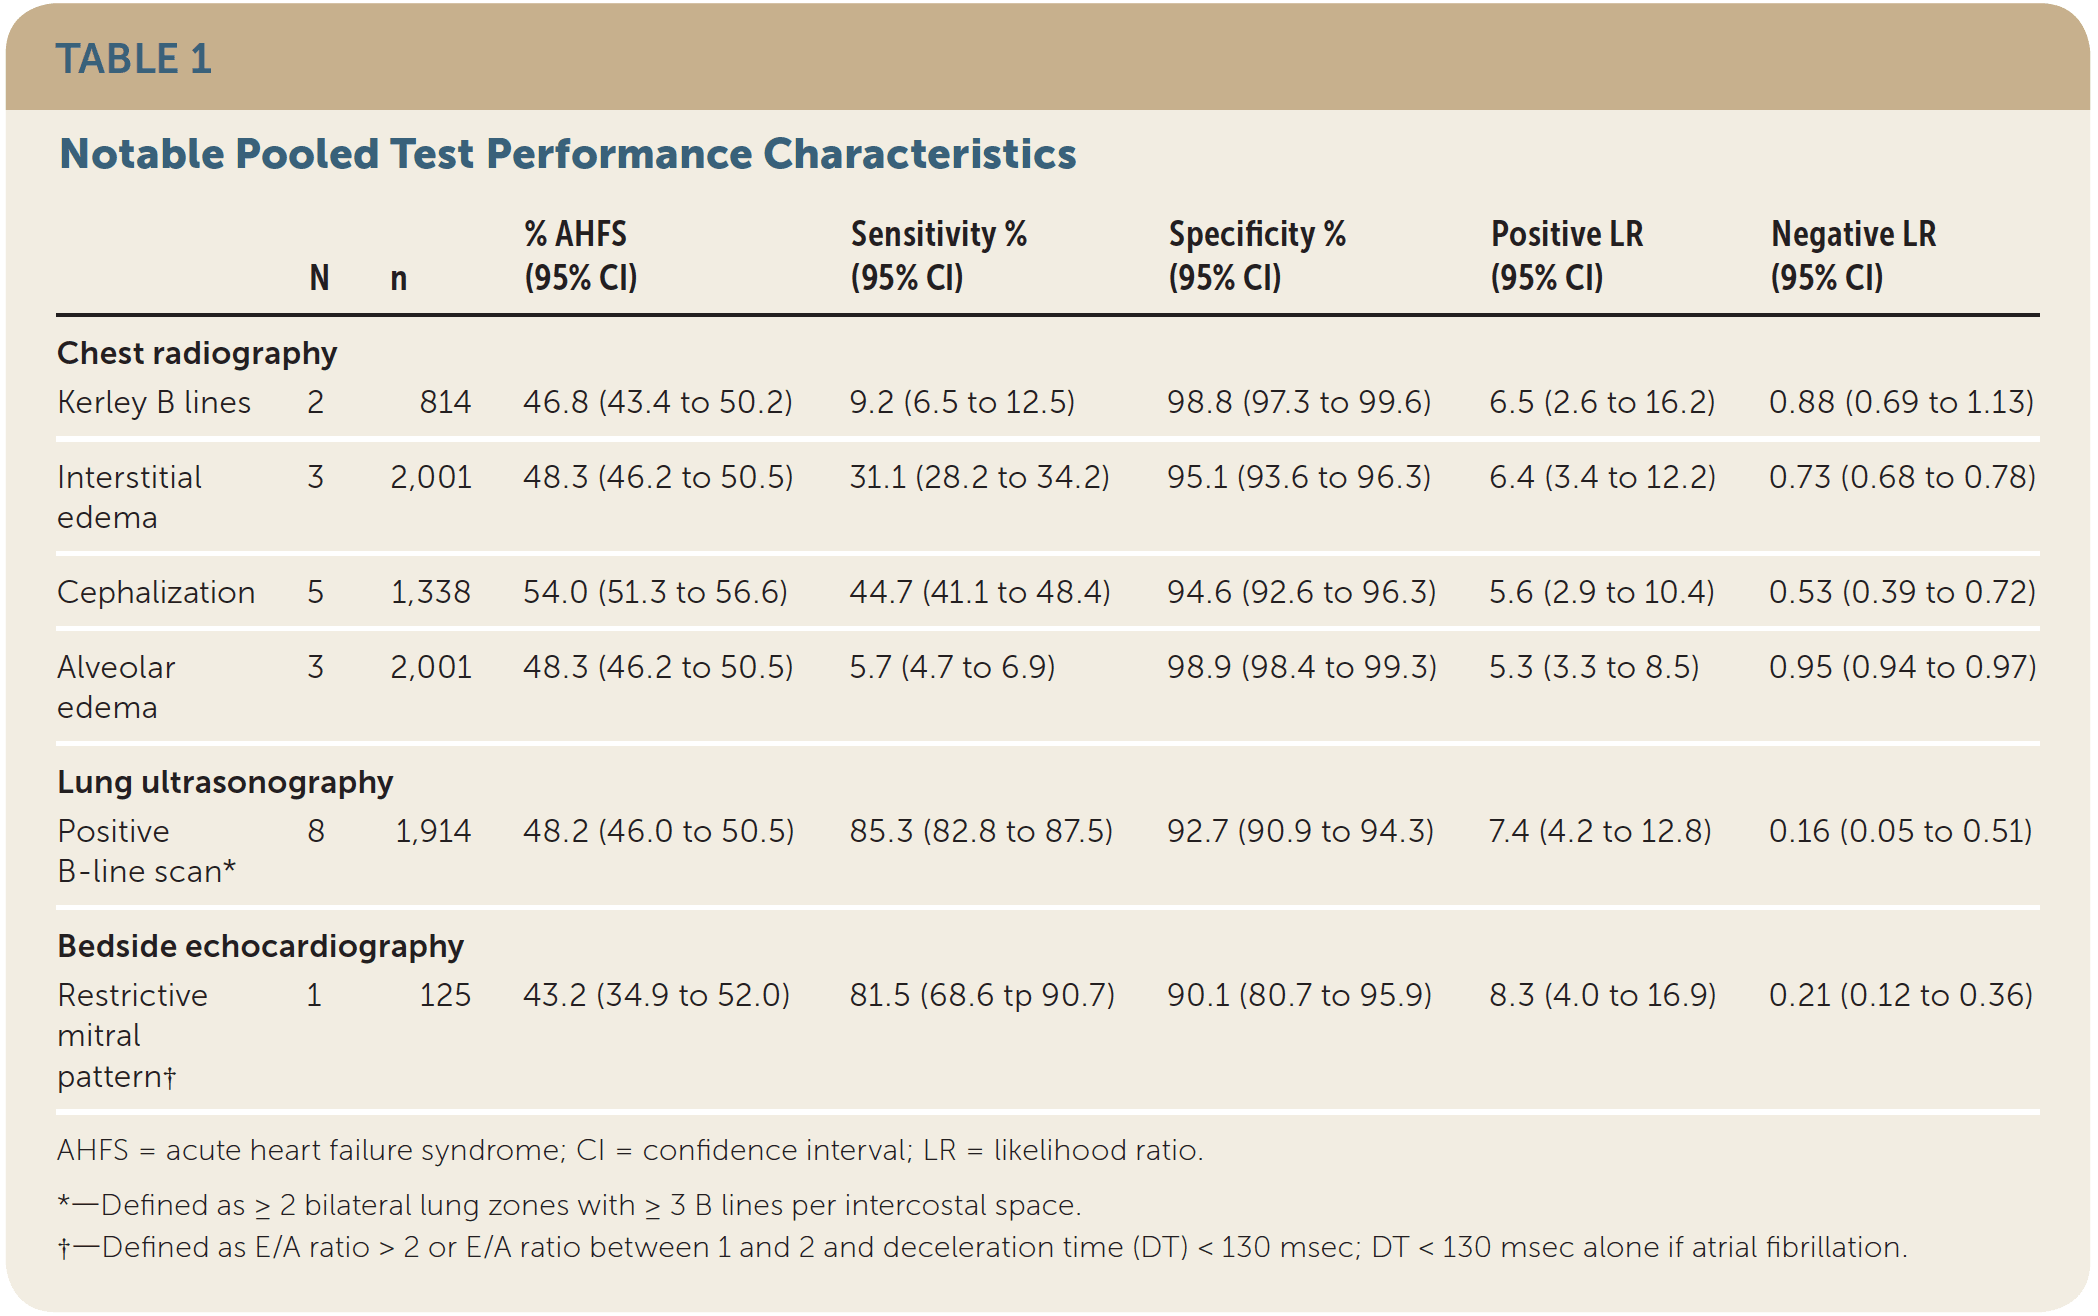
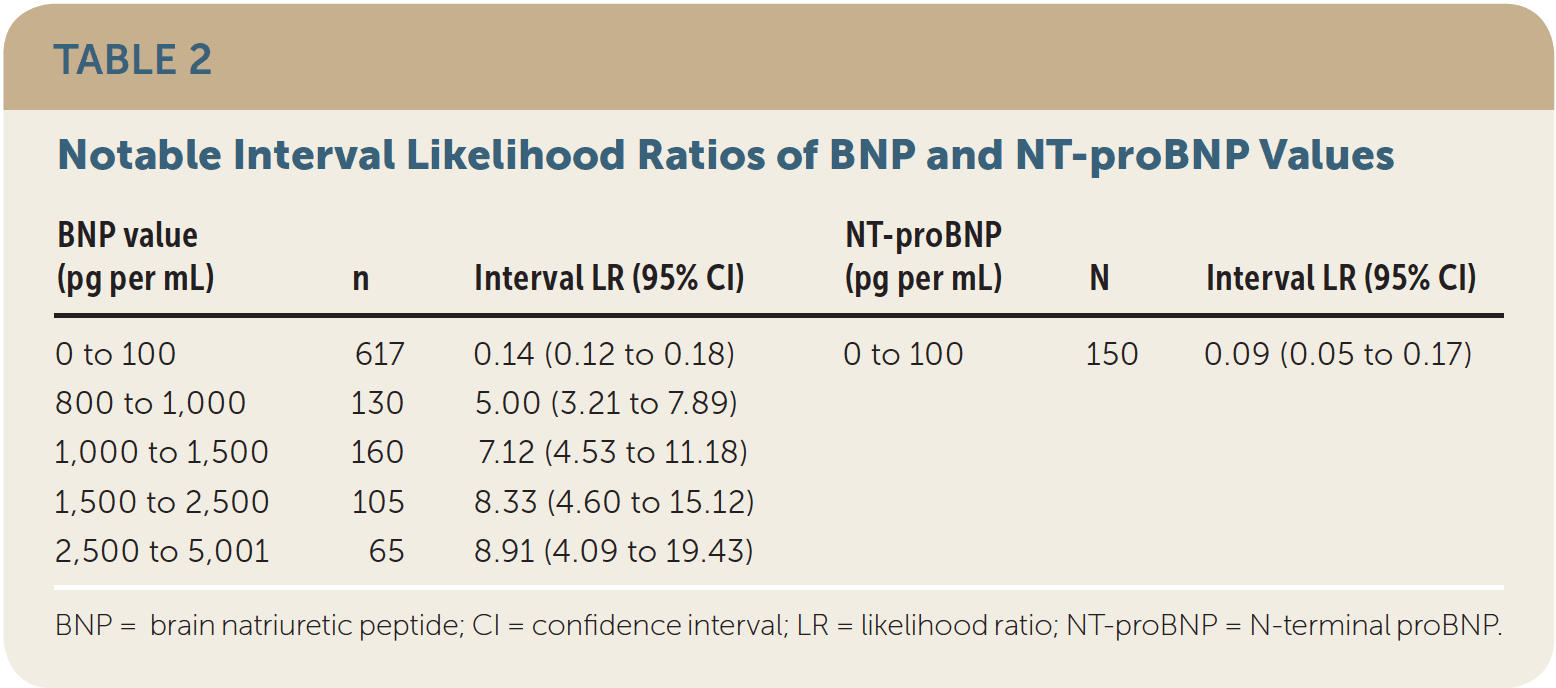
Serum B-type natriuretic peptide (BNP) testing increased the probability of AHFS (LR+ > 5.0) but only at markedly elevated concentrations (more than 800 pg per mL [800 ng per L]; Table 2); both BNP and serum N-terminal proB-type natriuretic peptide (NT-proBNP) testing were useful at excluding AHFS at very low concentrations (less than 100 pg per mL [100 ng per L]). Bedside lung ultrasonography of three or more B-line artifacts in two bilateral lung zones had the greatest discriminatory value among index tests (LR+ = 7.4; 95% CI, 4.2 to 12.8; negative likelihood ratio [LR–] = 0.16; 95% CI, 0.05 to 0.51). Bedside echocardiography of visually estimated reduced ejection fraction was somewhat helpful (LR+ = 4.1; 95% CI, 2.4 to 7.2), and the finding of restrictive mitral pattern was highly predictive of AHFS (LR+ = 8.3; 95% CI, 4.0 to 16.9).
Caveats
The estimation of each index test’s diagnostic accuracy was limited by the lack of a true, objective criterion or “gold” standard against which the test was measured. The criterion standard for AHFS was typically a subjective assessment by two or more physicians with data from the clinical record. The review did not evaluate the diagnostic accuracy of historical elements, symptoms, or examination findings in combination, also known as clinical gestalt.2 Clinical gestalt likely outperforms these diagnostic elements in isolation and plays an important role in determining the pretest probability of AHFS.
The studies that were included in the review varied in quality.2 Differences in inclusion and exclusion criteria among the included studies put them at varying degrees of risk for spectrum bias, and the consideration of pooled results should factor in the moderate to high statistical heterogeneity among included studies. With regards to the natriuretic peptide analyses, this review did not consider age as a variable that may alter BNP and NT-proBNP values. Age-stratified NT-proBNP cut points have since been demonstrated to be moderately useful in the diagnosis of AHFS.3
The accuracy of lung ultrasonography will be provider dependent, but emergency physician sonographers in most included studies were workshop-trained only. Furthermore, trainees may rapidly achieve procedural competency,4 and lung ultrasonography has been shown to have fair predictive value for pulmonary edema from AHFS when performed by novices and experts.5 Lastly, the performance of lung ultrasonography is likely time-sensitive because B-line artifacts appear to decrease coincident with treatment for lung edema caused by AHFS6 or other etiology.7
Conclusion: The individual components of the clinical history and physical examination, ECG, and chest radiography are not useful independently for confirming or excluding the diagnosis of AHFS in patients presenting to the emergency department. BNP concentrations above 800 pg per mL are helpful for establishing the diagnosis. BNP and NT-proBNP results are also valuable in ruling out AHFS when concentrations are below the threshold of 100 pg per mL. Lung ultrasonography, although provider-dependent, may be learned quickly and appears to have the best combination of test characteristics to confirm or exclude the diagnosis of AHFS.
The original manuscript was published in Medicine by the Numbers, American Family Physician as part of the partnership between TheNNT.com and AFP.
Published/Updated
What are Likelihood Ratios?
LR, pretest probability and posttest (or posterior) probability are daunting terms that describe simple concepts that we all intuitively understand.
Let's start with pretest probability: that's just a fancy term for my initial impression, before we perform whatever test it is that we're going to use.
For example, a patient with prior stents comes in sweating and clutching his chest in agony, I have a pretty high suspicion that he's having an MI – let's say, 60%. That is my pretest probability.
He immediately gets an ECG (known here as the "test") showing an obvious STEMI.
Now, I know there are some STEMI mimics, so I'm not quite 100%, but based on my experience I'm 99.5% sure that he's having an MI right now. This is my posttest probability - the new impression I have that the patient has the disease after we did our test.
And likelihood ration? That's just the name for the statistical tool that converted the pretest probability to the posttest probability - it's just a mathematical description of the strength of that test.
Using an online calculator, that means the LR+ that got me from 60% to 99.5% is 145, which is about as high an LR you can get (and the actual LR for an emergency physician who thinks an ECG shows an obvious STEMI).
(Thank you to Seth Trueger, MD for this explanation!)